

pH changes by more than five units along the gut, so where a compound dissolves shapes how much of a dose reaches the blood
An oral dose from stomach to colon: how pH sets solubility and lipophilicity, when the dose itself becomes the limit, and how gut wall, liver and bacteria change what circulates.
Related: nine botanical actives on the general solubility equation · bioavailability design
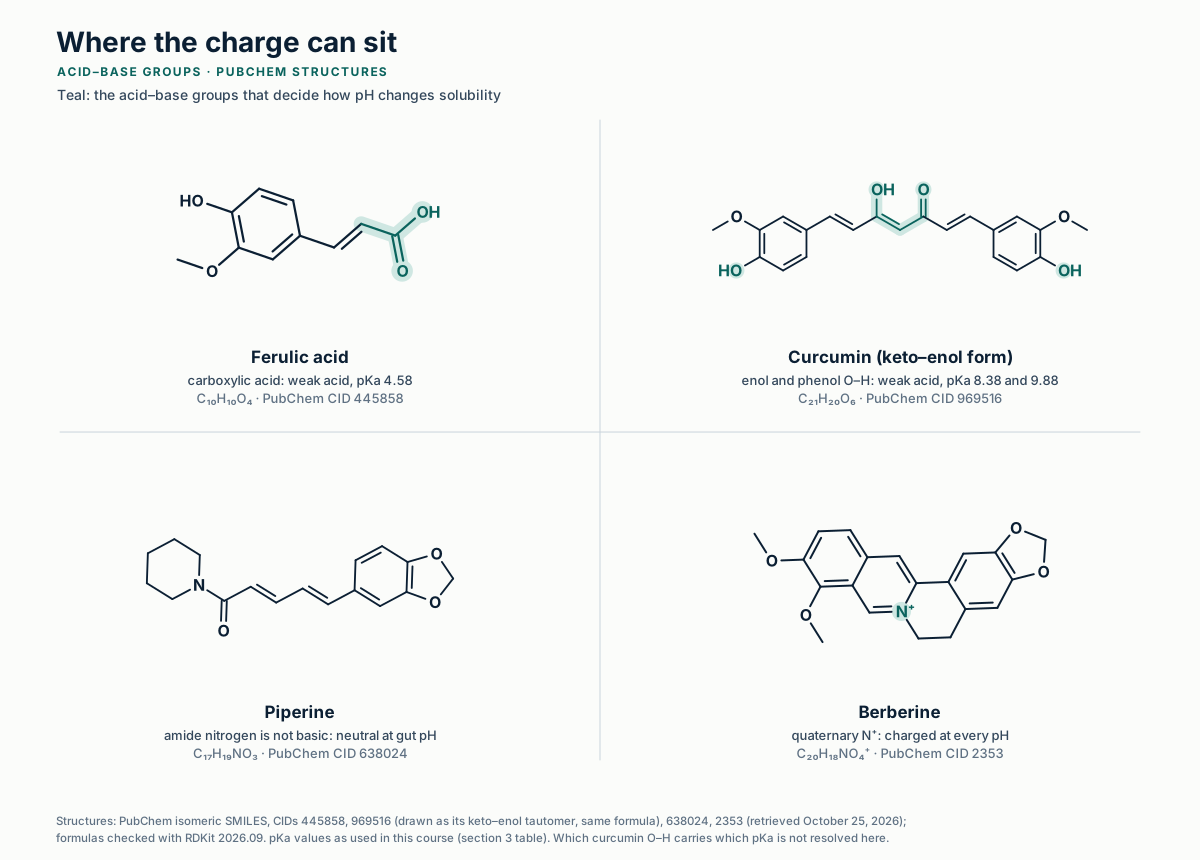
Four compounds span the acid–base range, from ferulic acid to berberine, which is charged at every pH
Data table: the four compounds
| Compound | PubChem CID | Formula | Acid–base behavior used in this course |
|---|---|---|---|
| Ferulic acid | 445858 | C10H10O4 | Weak acid, pKa 4.58 |
| Curcumin | 969516 | C21H20O6 | Weak acid, pKa 8.38 and 9.88 |
| Piperine | 638024 | C17H19NO3 | No ionizable group (neutral) |
| Berberine | 2353 | C20H18NO4+ | Quaternary nitrogen: charged at every pH |
Drag or use the arrow keys to rotate; the charge sits on berberine's ring nitrogen at every pH.
You will learn
- How pH, transit time and fluid volume change from stomach to colon.
- How to predict the solubility of acids, bases, ampholytes and permanent ions from pKa.
- What log D, the dose number and the ICH M9 solubility test tell you.
- Why dissolved compounds can still precipitate, be pumped back or be metabolized.
- How gut bacteria and dose size change exposure, with real human data.
Status. EUTECNIQ has no laboratory or data of its own. Results shown are published third-party studies; calculators are educational models.
pH rises from about 1.7 in the fasted stomach to 7.5 in the terminal ileum, then drops again in the caecum
A tablet meets acid for roughly an hour, near-neutral fluid for several hours, then a bacterial ecosystem. Water is scarce and sits in separate pockets.
Text version of the gut map
Stomach. pH 1.0–2.5 when fasted. A 240 mL glass of water was half emptied in 13 ± 1 min; a pH capsule stayed 1.1 h (median). Resting water 35 ± 7 mL. Weak bases ionize and dissolve; weak acids stay neutral.
Duodenum. pH about 6; bile and pancreatic juice enter. Weak acids ionize; bile-salt micelles take up lipophilic compounds.
Jejunum and ileum. pH 6.6 rising to 7.5. Small-intestinal transit was about 3 h for dosage forms by scintigraphy and 8 h (median) for a pH capsule. Fasted water 43–105 mL in two MRI studies, held in separate pockets. The main absorbing surface, with conjugating enzymes and P-glycoprotein in the epithelium.
Caecum and colon. pH 5.7–6.4 in the caecum, rising to 6.6–7.0 toward the rectum. Colonic transit of a pH capsule 17.5 h (median); free water about 13 mL. Bacteria transform what was not absorbed.
Show the data: gastrointestinal pH
| Segment | pH | Statistic | Study |
|---|---|---|---|
| Stomach, fasted | 1.0–2.5 | range, all subjects | Evans et al. 1988 |
| Stomach, fasted | 1.7 | median | Dressman et al. 1990 |
| Stomach after a meal | 6.7 | median peak; back to fasted value in under 2 h | Dressman et al. 1990 |
| Duodenum, fasted | 6.1 | median | Dressman et al. 1990 |
| Duodenum, after a meal | 5.4 | median | Dressman et al. 1990 |
| Duodenum | 6.4 | reported value | Fallingborg et al. 1989 |
| Proximal small intestine | 6.6 ± 0.5 | mean ± SD, first hour | Evans et al. 1988 |
| Terminal ileum | 7.5 ± 0.4 | mean ± SD | Evans et al. 1988 |
| Distal small intestine | 7.3 | reported value | Fallingborg et al. 1989 |
| Caecum | 6.4 ± 0.4 | mean ± SD | Evans et al. 1988 |
| Caecum | 5.7 | reported value | Fallingborg et al. 1989 |
| Left colon, final value | 7.0 ± 0.7 | mean ± SD | Evans et al. 1988 |
| Rectum | 6.6 | reported value | Fallingborg et al. 1989 |
Explanation, details and sources
Food changes the picture. After a meal the stomach briefly reached pH 6.7, while the duodenum fell to 5.4 and stayed below its fasted value for the 4 hours observed (Dressman et al. 1990).
For a product decision. Release site matters. A weak acid released in the stomach meets its lowest solubility first; a weak base meets its highest, then risks precipitating once it empties (section 5). Fasted and fed testing can give different answers for the same capsule.
Weak acids dissolve more as pH rises above their pKa, weak bases as it falls below theirs, and permanent ions follow neither rule
Avdeef A. Adv Drug Deliv Rev. 2007;59:568–590; Avdeef A. Absorption and Drug Development, 2nd ed. Wiley; 2012. For an ampholyte, pKa1 < pKa2 are the macroscopic constants on either side of the neutral (or zwitterionic) form.
Show the data: berberine chloride solubility
| Medium | 25 °C, mM | 37 °C, mM |
|---|---|---|
| Water | 5.27 ± 0.29 | 8.50 ± 0.40 |
| Phosphate buffer pH 7.0 | 4.05 ± 0.09 | 9.69 ± 0.37 |
| HCl pH 1.2; phthalate pH 3.0 and 5.0; borate pH 9.0 | "nearly 20-fold lower" than pH 7.0 phosphate | not reported |
| Phosphate salts at every pH from 2.0 to 9.0 | pH-independent (data not shown in the paper) | not reported |
Battu et al. 2010, Results. The paper also reports an experimental log P of −1.5 (shake flask) against computed values of −0.9 to −2.2.
| Segment | pH | Solubility | S/S0 | Dose number |
|---|---|---|---|---|
| Stomach, fasted | 1.7 | |||
| Duodenum | 6.1 | |||
| Proximal small intestine | 6.6 | |||
| Terminal ileum | 7.5 | |||
| Caecum | 6.4 |
Method, assumptions and limits
- What it calculates
- Total equilibrium solubility at each pH, its gain over the neutral form, the dose number in each segment, and the lowest solubility over pH 1.2–6.8 with the volume needed to dissolve the dose there.
- Equations
- Acid: S = S0(1 + 10pH−pKa1 + 102pH−pKa1−pKa2), the last term only for two-pKa acids; base: S = S0(1 + 10pKa1−pH); ampholyte: S = S0(1 + 10pKa1−pH + 10pH−pKa2); neutral and permanent ions: S = S0. Then S = min(S, ceiling). Do = dose/(250 mL × S). Volume = dose/Smin.
- Variables and units
- S0, ceiling and S in µg/mL (sliders are log10); dose in mg (log10 slider); volume in mL.
- Assumptions
- Equilibrium with one solid form; activity effects, common-ion effects, buffer capacity, bile micelles and temperature ignored. The pH at which the lowest solubility occurs is found exactly: S(pH) is convex, so the minimum sits at pH 1.2, at 6.8 or, for an ampholyte, at the mean of its two pKa values.
- Valid range
- pKa 0–14. Real profiles often depart from this shape; Bergström and Avdeef (2019) show salts, aggregates and buffer interactions distorting measured curves.
- What it does not establish
- The solubility of any real ingredient (S0 is your input), dissolution rate, absorption or bioavailability. ICH M9 classification applies to drugs and requires measured data at 37 ± 1 °C.
- References
- Avdeef 2007 and 2012; Bergström & Avdeef 2019; Amidon et al. 1995; ICH M9 (2019); pKa sources in the section 3 table.
- Verification
- Unit tests (
tests/unit/acsol.test.js) and an independent Python reference (tests/numerics/ref/academy_solubility-and-ph.py) recompute every readout.
Explanation, details and sources
The pKa is the pH at which half the molecules carry a charge. Charged molecules are far more soluble in water than neutral ones, so total solubility S grows tenfold for every pH unit past the pKa.
Base: S = S0(1 + 10pKa − pH)
Ampholyte: S = S0(1 + 10pKa1 − pH + 10pH − pKa2)
at saturation [HA] = S0
S = [HA] + [A⁻] = S0(1 + Ka/[H⁺])
Berberine shows the limit of the equation. Its nitrogen is quaternary, so it is charged at every pH; Battu and colleagues found its chloride nearly 20 times less soluble in hydrochloric acid, phthalate and borate buffers than in pH 7.0 phosphate, yet pH-independent when every buffer was made from phosphate salts.
Limits. Measured curves often bend away from the equation through salts, aggregates and buffer interactions. Normalized for pH and temperature, 34 published studies of diclofenac gave its intrinsic solubility with a standard deviation of 0.18 log units, so careful measurements do agree when conditions are stated (Bergström and Avdeef 2019).
Calculator 1 · pH–solubility profile, GI map and dose number
Pick a compound to load its measured pKa values, then set the intrinsic solubility and the dose. Presets fill in pKa only; S0 and dose are your inputs.
Once a compound is mostly ionized, log D falls by one unit for every pH unit
Show the data: pKa and log P of the ten compounds
| Compound (PubChem CID) | Type | pKa | log P | Sources and status |
|---|---|---|---|---|
| Salicylic acid (338) | acid | 2.98 (20 °C) | 2.26 | pKa: CRC Handbook via HSDB; log Kow: Hansch et al. 1995 via HSDB. Measured. |
| Gallic acid (370) | acid | 4.40 | 0.70 | pKa: Patty 1963 via HSDB; log Kow: Hansch et al. 1995. Measured. |
| Ferulic acid (445858) | acid | 4.58 | 1.51 | pKa: Serjeant & Dempsey 1979 via HSDB; log Kow: Hansch et al. 1995. Measured. |
| Caffeic acid (689043) | acid | 4.62 (25 °C) | 1.15 | pKa: Serjeant & Dempsey 1979 via HSDB; log Kow: Sangster 1993 via HSDB. Measured. |
| Quercetin (5280343) | acid, two pKa | 7.03; 9.15 | 2.35 | pKa: Sauerwald et al. 1998 (UV-visible, measured). log D7.4 1.82 ± 0.32 measured (Rothwell et al. 2005); log P derived from it. |
| Curcumin (969516) | acid, three pKa | 8.38; 9.88; 10.51 | 3.2 | pKa: Bernabé-Pineda et al. 2004 (measured). log P: XLogP3, PubChem (predicted). |
| Ephedrine (9294) | base | 9.65 (25 °C) | 1.13 | Both from Avdeef 2012 via HSDB. Measured. Chemistry only. |
| Caffeine (2519) | very weak base | 0.7 (cation) | −0.07 | pKa: Svorc 2013 via HSDB; log Kow: Hansch et al. 1995. Measured. |
| Berberine (2353) | permanent cation | none | −1.5 | Battu et al. 2010: "permanently charged", shake-flask log P of the chloride (apparent). |
| Piperine (638024) | neutral (amide) | none in the gut range | 3.5 | log P: XLogP3, PubChem (predicted). |
PubChem compound records (Dissociation Constants and LogP sections, accessed October 23, 2026); HSDB entries cite the original sources named.
Show the data: computed log D values
| Compound | pH 1 | 2 | 3 | 4 | 5 | 6 | 6.5 | 7 | 7.5 | 8 |
|---|---|---|---|---|---|---|---|---|---|---|
| Salicylic acid | 2.3 | 2.2 | 1.9 | 1.2 | 0.2 | −0.8 | −1.3 | −1.8 | −2.3 | −2.8 |
| Gallic acid | 0.7 | 0.7 | 0.7 | 0.6 | 0.0 | −0.9 | −1.4 | −1.9 | −2.4 | −2.9 |
| Ferulic acid | 1.5 | 1.5 | 1.5 | 1.4 | 1.0 | 0.1 | −0.4 | −0.9 | −1.4 | −1.9 |
| Caffeic acid | 1.1 | 1.1 | 1.1 | 1.1 | 0.6 | −0.2 | −0.7 | −1.2 | −1.7 | −2.2 |
| Quercetin | 2.3 | 2.3 | 2.3 | 2.3 | 2.3 | 2.3 | 2.2 | 2.1 | 1.7 | 1.3 |
| Curcumin | 3.2 | 3.2 | 3.2 | 3.2 | 3.2 | 3.2 | 3.2 | 3.2 | 3.1 | 3.0 |
| Ephedrine | ≤ −3 | ≤ −3 | ≤ −3 | ≤ −3 | ≤ −3 | −2.5 | −2.0 | −1.5 | −1.0 | −0.5 |
| Caffeine | −0.2 | −0.1 | −0.1 | −0.1 | −0.1 | −0.1 | −0.1 | −0.1 | −0.1 | −0.1 |
| Berberine | −1.5 | −1.5 | −1.5 | −1.5 | −1.5 | −1.5 | −1.5 | −1.5 | −1.5 | −1.5 |
| Piperine | 3.5 | 3.5 | 3.5 | 3.5 | 3.5 | 3.5 | 3.5 | 3.5 | 3.5 | 3.5 |
Calculator 2 · log D across the gut
Method, assumptions and limits
- What it calculates
- log D and the un-ionized share at any pH, and at the fasted stomach and proximal small-intestine reference pH.
- Equations
- log D = log P − log10 r(pH), with r the ionization ratio of section 2; un-ionized share = 1/r. For a permanent ion, log D equals the entered value at every pH.
- Variables and units
- pKa and pH dimensionless; log P and log D are log10 of octanol/water concentration ratios.
- Assumptions
- Only the neutral species enters octanol; no ion pairs, no self-association; 25 °C constants used at body temperature.
- Valid range
- Readouts below −4 are floored and flagged, because ion-pair partitioning dominates there.
- What it does not establish
- Permeability, absorption or bioavailability. Lipophilicity raises membrane passage but also first-pass loss: across 309 drugs, the fractions escaping gut-wall and liver elimination fell as lipophilicity rose (Varma et al. 2010).
- References
- Scherrer & Howard 1977; Avdeef 2012; Rothwell et al. 2005; Varma et al. 2010; constant sources in the table above.
- Verification
- Unit tests and the Python reference check log D at the pKa (log P − log 2), at large ionization, and the quercetin back-calculation.
Explanation, details and sources
log P describes how the neutral form splits between octanol and water. log D counts every species in the water, so it changes with pH (Scherrer and Howard 1977). Membranes pass neutral molecules most easily, the idea behind the pH-partition hypothesis (Shore et al. 1957).
A common misreading. Rothwell and colleagues reported quercetin's "log P" as 1.82, but they measured it at pH 7.4, where about 70% of quercetin is ionized. It is a log D. The derived neutral log P is about 0.5 units higher.
If one dose cannot dissolve in 250 mL at every pH from 1.2 to 6.8, solubility can cap absorption
Explanation, details and sources
ICH M9 states: "A drug substance is classified as highly soluble if the highest single therapeutic dose is completely soluble in 250 ml or less of aqueous media over the pH range of 1.2–6.8 at 37±1°C." The lowest solubility in that range decides.
Worked example. Battu and colleagues noted that at about 2.0 mg/mL, a 100 mg dose of berberine chloride needs over 50 mL of water. Its dose number in water is therefore 100 ÷ (250 × 1.96) = 0.20. In the hydrochloric acid buffer, nearly 20 times less soluble, the same arithmetic gives about 4: the dose would no longer dissolve in 250 mL.
M9 lists caffeine among its model drugs of high permeability. It is a drug guideline: no supplement ingredient is classified this way. The maximum absorbable dose calculator adds permeability and transit, and the delivery tool estimates S0 from log P and melting point.
Dissolution speed scales with surface area and the solubility gap, so a weak base can dissolve in the stomach and precipitate in the intestine
Explanation, details and sources
Noyes and Whitney (1897) found that a solid dissolves at a rate proportional to how far the solution is from saturation. When a dissolved weak base empties into pH 6.6, the solution can hold more than its new equilibrium solubility for a while, then crystallize.
Precipitation inhibitors in a formulation aim to stretch the parachute (Brouwers et al. 2009). Whether they do so in people is an empirical question for each product.
A dissolved compound must still cross the gut wall and survive the liver, and each step multiplies the loss
Text version of the absorption schematic
Dissolved molecules in the small intestine cross enterocytes mainly as the neutral form. P-gp on the apical membrane can pump some back. Enterocytes conjugate some compounds into glucuronides and sulfates (UGT and SULT enzymes), so only a fraction Fg escapes the gut wall. The portal vein carries the rest to the liver, which conjugates and oxidizes more (Fh) and secretes some compounds into bile. What reaches the systemic blood is F = Fa × Fg × Fh of the dose. Unabsorbed material passes to the colon. In rats, berberine's absolute oral bioavailability was 0.36% and about half of the dose was lost in the small intestine; P-gp inhibitors raised its absorption 6-fold in perfused rat intestine. In people given 10 or 12 g of curcumin, free curcumin was detected in 1 of 12 subjects, while glucuronide and sulfate conjugates were found in all, at a ratio of 1.92 to 1.
Explanation, details and sources
Oral bioavailability is the product of three fractions: absorbed, escaping the gut wall and escaping the liver (Varma et al. 2010). P-glycoprotein (P-gp), an efflux pump on the luminal side of intestinal cells, returns some molecules to the gut (Thiebaut et al. 1987).
Piperine raised serum curcumin in an eight-person study, but a 30-person crossover found no gain in total curcuminoids
Show the data: piperine and curcumin studies
| Study | Design | Analyte | Result |
|---|---|---|---|
| Shoba et al. 1998, rats | curcumin 2 g/kg, piperine 20 mg/kg | serum curcumin | bioavailability +154%; higher concentration for 1–2 h |
| Shoba et al. 1998, humans | n = 8; 2 g curcumin, 20 mg piperine; sampling 6 h (COT 2024) | serum curcumin | +2000%; curcumin alone "undetectable or very low" |
| Fança-Berthon et al. 2021 | n = 30, randomized open-label crossover; piperine product (1,500 mg of a 95% curcuminoid extract plus 15 mg of a 95% piperine extract) vs a standard 95% curcuminoid extract (1,500 mg) from another supplier; 24 h | 15 curcuminoids and metabolites | AUC0–24 h 4,380 ± 2,330 vs 5,080 ± 2,410 ng·h/mL; relative bioavailability 1.1 ± 0.79; not significant |
| Same study | as above | 9 curcumin metabolites | relative bioavailability 1.1 ± 0.81 |
| Same study | as above | unconjugated parent curcuminoids | AUC0–24 h 80.3 ± 176 vs 64.4 ± 123 ng·h/mL |
Explanation, details and sources
Shoba and colleagues (1998) gave piperine, "a known inhibitor of hepatic and intestinal glucuronidation", with 2 g of curcumin and reported a 2000% increase in bioavailability. The UK Committee on Toxicity notes that curcumin alone was below the detection limit and that it is not clear how those non-detects entered the AUC.
The mechanism carries a second consequence. In vitro, piperine inhibited P-gp transport of digoxin (IC50 15.5 µM) and CYP3A4 (Bhardwaj et al. 2002), so it can raise exposure to drugs as well. Higher exposure is not efficacy. Combination science and Evidence and pharmacokinetics cover interactions and liver-injury reports.
Gut bacteria finish the chemistry for some compounds, so exposure depends on which microbes a person carries
The compound that reaches the blood may be one the plant never made. Two people taking the same dose can form different metabolites, or none.
Show the data: producer prevalence
| Group | Share | Source |
|---|---|---|
| Urolithin metabotype A (urolithin A conjugates only) | 25–80% of volunteers | Tomás-Barberán et al. 2014 |
| Metabotype B (isourolithin A and/or urolithin B as well) | 10–50% | Tomás-Barberán et al. 2014 |
| Metabotype 0 (none detected) | 5–25% | Tomás-Barberán et al. 2014 |
| Equol producers, Western adults | 25–30% | Setchell & Clerici 2010 |
| Equol producers, adults in Japan, Korea or China, and Western vegetarians | 50–60% | Setchell & Clerici 2010 |
| Vegetarians (n = 29) vs non-vegetarians (n = 12) | 59% vs 25% | Setchell & Cole 2006 |
Exposure can rise faster or slower than the dose, and the direction points to the step that saturates
Show the data: dose and exposure
| Study | Dose | Exposure |
|---|---|---|
| Chow et al. 2001, EGCG | 200 / 400 / 600 / 800 mg | AUC 22.5 / 35.4 / 101.9 / 167.1 min·µg/mL |
| Chow et al. 2001, Polyphenon E | 200 / 400 / 600 / 800 mg EGCG | AUC 21.9 / 52.2 / 79.7 / 161.4 min·µg/mL |
| Cheng et al. 2001, curcumin | 4 / 6 / 8 g per day | peak serum 0.51 ± 0.11 / 0.63 ± 0.06 / 1.77 ± 1.87 µM |
| Vareed et al. 2008, curcumin conjugates | 10 / 12 g, n = 6 each | AUC 35.33 ± 3.78 / 26.57 ± 2.97 µg·h/mL (mean ± SE); Cmax 2.30 / 1.73 µg/mL |
From 200 to 800 mg, EGCG AUC rose 7.4-fold for a 4-fold dose (our arithmetic from the published means).
Method, assumptions and limits
- What it calculates
- Plasma concentration after one oral dose, Cmax, Tmax, AUC0–∞, the fraction absorbed, AUC relative to the linear model, and the AUC ratio for a doubled dose.
- Equations
- dA/dt = −ra − ktA; V·dC/dt = ra − re. Linear: ra = kaA, re = CL·C. Saturable elimination: re = CL·C/(1 + C/Km), i.e. Vmax = CL·Km. Saturable absorption: ra = kaA/(1 + A/Km).
- Variables and units
- Dose and A in mg; C in mg/L; ka, kt in h⁻¹; V in L; CL in L/h; Km in mg/L for elimination and mg (amount in the gut) for absorption. Dose, ka, V, CL and Km sliders are log10.
- Assumptions
- One well-mixed compartment; one saturable step at a time; unabsorbed drug lost first-order; no metabolites, protein binding or enterohepatic recycling. Integrated by fourth-order Runge–Kutta; after the gut is empty the remaining AUC is added analytically.
- Valid range
- Within the slider limits. Default kt 0.3 h⁻¹ corresponds to a 3.3 h small-intestinal transit.
- What it does not establish
- The kinetics of any compound, a safe or effective dose, or the exposure from any product. Real nonlinearity must be shown with dose-ranging data like the studies above.
- References
- Ludden 1991 (sources of nonlinearity); Chow et al. 2001; Davis et al. 1986 (transit).
- Verification
- Unit tests compare the linear mode with the analytic Bateman solution and the fast-absorption limit with the Michaelis–Menten bolus result AUC = (C0/Vm)(Km + C0/2). The Python reference integrates the same equations with SciPy's LSODA solver.
Explanation, details and sources
When an enzyme or transporter saturates, pharmacokinetics become nonlinear: concentrations rise disproportionately high or low relative to the dose (Ludden 1991). Saturated first-pass metabolism or elimination bends exposure upward; saturated uptake or dissolution bends it downward.
Worked example. Divide each EGCG AUC by its dose: 0.11 min·µg/mL per mg at 200 mg and 0.21 at 800 mg. Exposure per milligram nearly doubled. A safety margin set from a low-dose study would therefore overstate the margin at a high dose; Course 9 builds on this.
Calculator 3 · One-compartment oral model with a saturable step
All three modes match at low dose. Switch the mode and raise the dose to see which way AUC bends.
Five distinctions keep a solubility or bioavailability claim honest
- Dispersibility, droplets or particles suspended≠Solubility, molecules dissolved
- Bioaccessibility, released in the gut≠Systemic bioavailability, reaching the blood
- Higher exposure≠Efficacy, or a wider safety margin
- "log P" measured at pH 7.4≠log P of the neutral form
- Low exposure≠Poor solubility alone: curcumin about 90% decomposed within 30 min in pH 7.2 buffer at 37 °C (Wang et al. 1997)
Ten terms used in this course
Show the 10 key terms
- pKa
- The pH at which half the molecules of a group are ionized.
- Intrinsic solubility, S0
- Solubility of the neutral form alone.
- Ampholyte
- A molecule with both an acidic and a basic group.
- log P
- Octanol–water partition of the neutral form, as log10.
- log D
- The same ratio counting every species, at a stated pH.
- Dose number
- Dose divided by what 250 mL can dissolve.
- Supersaturation
- Dissolved concentration above equilibrium solubility; it tends to precipitate.
- First-pass metabolism
- Loss in the gut wall and liver before systemic circulation.
- P-glycoprotein
- An efflux pump that returns some molecules to the gut lumen.
- Nonlinear pharmacokinetics
- Exposure that does not scale in proportion to dose.
Five questions on pH, dose and exposure
Ferulic acid has a pKa of 4.58. Is it more soluble in the fasted stomach or the small intestine?
The small intestine. At pH 6.6 it sits two pH units above its pKa, so its total solubility is about 100 times that of the neutral form; at pH 1.7 it is almost entirely neutral.
Why does berberine's solubility not follow the Henderson–Hasselbalch curve?
Its nitrogen is quaternary, so it is charged at every pH. Its solubility changed with the buffer ions and temperature, and was pH-independent when every buffer used phosphate salts (Battu et al. 2010).
A dose has a dose number of 0.2 at pH 6.8 and 40 at pH 1.2. Is it highly soluble under ICH M9?
No. M9 classifies on the lowest solubility over pH 1.2–6.8, and at pH 1.2 the dose would need 40 × 250 mL to dissolve.
EGCG exposure rose 7.4-fold when the dose rose 4-fold. What does that suggest?
A saturable loss: a process that removes a smaller share at higher doses. Chow and colleagues suggested saturable presystemic elimination. It also means exposure from a high dose cannot be extrapolated linearly from a low one.
Two people take the same soy isoflavone dose; only one forms equol. Why?
Equol is made by gut bacteria that only some adults carry: about 25–30% of Western adults and 50–60% of adults in Japan, Korea or China (Setchell and Clerici 2010).
Continue with toxicology and dose
Course 9 turns exposure into safety margins.